
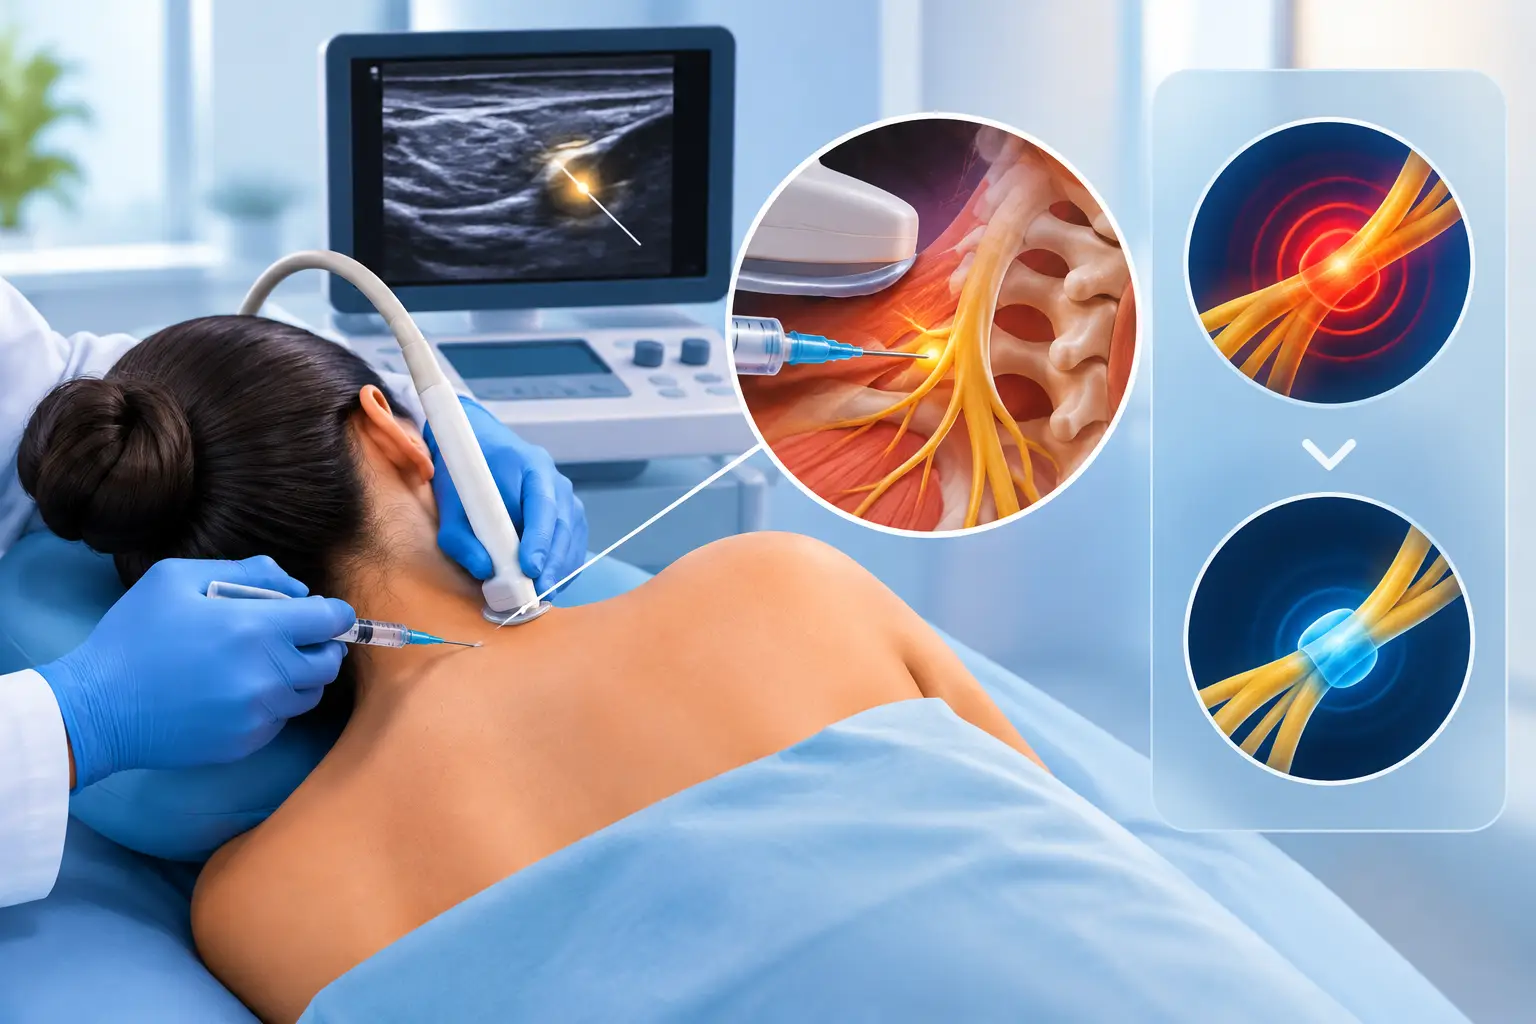
A scan may show arthritis, a disc bulge, or post-surgical changes, yet still leave one critical question unanswered: which structure is actually causing the pain? Diagnostic nerve blocks help answer that question. By temporarily numbing a carefully selected nerve or joint area, a pain specialist can determine whether that location is driving symptoms and use the response to plan more precise care.
For people living with persistent back, neck, joint, or nerve pain, this can be a meaningful shift. Rather than treating every abnormality seen on imaging or relying on broad medication-based approaches, diagnostic testing can help narrow the focus to the pain generator most likely to benefit from treatment.
What Are Diagnostic Nerve Blocks?
A diagnostic nerve block is a minimally invasive injection used primarily to identify the source of pain. It usually contains a small amount of local anesthetic, sometimes with contrast dye to confirm accurate placement under imaging. Unlike a therapeutic injection intended to provide longer-term relief, the main purpose is to observe what happens when a specific nerve pathway or joint is temporarily numbed.
If the targeted area is responsible for a patient’s usual pain, the patient may experience substantial but temporary relief during the anesthetic’s expected duration. That response gives the physician useful clinical evidence. If the pain does not change, it may suggest that the treated structure is not the primary source, or that more than one pain generator is involved.
This distinction matters because chronic pain is rarely identical from one person to the next. A person with low back pain may have discomfort related to facet joints, the sacroiliac joints, a disc, spinal stenosis, muscle dysfunction, or a combination of factors. An MRI can provide valuable information, but it does not always establish which finding is responsible for the symptoms felt every day.
When a Diagnostic Nerve Block May Be Recommended
A pain management physician may recommend a diagnostic block when the history, examination, and imaging point toward a specific structure but cannot confirm it with confidence. These procedures are commonly used to evaluate suspected facet joint pain in the neck or back, sacroiliac joint pain, occipital nerve-related headaches, and certain nerve-related pain patterns after injury or surgery.
For example, facet joints are small joints along the spine that can become painful with arthritis, repetitive strain, injury, or age-related changes. A medial branch block numbs the small nerves that carry pain signals from those joints. If it produces a strong, short-lived reduction in the patient’s familiar pain, the result may support moving forward with radiofrequency ablation, a treatment designed to provide longer-lasting relief by interrupting those pain signals.
The procedure is not automatically the right next step for everyone. If symptoms are improving with physical therapy, activity modification, or other conservative care, a diagnostic block may not be necessary right away. It becomes more valuable when pain persists, function remains limited, and a targeted intervention is being considered.
A Diagnostic Test, Not a Promise of Permanent Relief
It is understandable to hope that any injection will eliminate pain. With diagnostic nerve blocks, however, short-term relief is often the expected outcome. The anesthetic may work for hours, occasionally longer, depending on the medication used and the individual response.
That temporary window is not a failure. It is the information the physician needs. A clear response can help avoid procedures aimed at the wrong area, while an unclear response may lead to a broader evaluation of other possible pain sources.
What Happens During the Procedure?
Diagnostic blocks are typically performed in an outpatient setting and often take only a short time. Before the procedure, the physician reviews symptoms, imaging, medications, allergies, and relevant health conditions. Patients should also discuss blood thinners, diabetes medications, active infections, and the possibility of pregnancy, since these factors may affect scheduling or preparation.
During the procedure, the patient is positioned comfortably on an examination table. The skin is cleaned, and a local anesthetic may be used to numb the entry site. Using fluoroscopy, a type of live X-ray guidance, the physician advances a thin needle toward the targeted nerve or joint. Contrast dye may be used to verify placement before the anesthetic is administered.
Image guidance is central to the value of the procedure. These targets are small and located near important structures, so precision helps improve both safety and the reliability of the diagnostic result. Patients may feel brief pressure or a pinch, but most diagnostic blocks do not require a lengthy recovery.
Many people return home the same day. Because temporary numbness or weakness can occur in the treated area, patients are commonly advised to arrange a ride and avoid driving until their physician says it is safe. Specific instructions vary based on the location of the block, medications used, and the patient’s medical history.
Your Pain Diary Can Make the Results More Useful
The hours after a diagnostic nerve block are often as important as the injection itself. The care team may ask patients to perform the movements or activities that usually bring on their pain, such as turning the head, standing from a chair, walking, climbing stairs, or extending the back.
Keeping a simple record of pain levels and function before and after the block helps separate a vague improvement from a meaningful response. Note the time the injection was performed, the percentage of relief experienced, how long it lasted, and whether you could complete an activity that is normally difficult.
For instance, being able to walk through a grocery store with much less low back pain may be more informative than reporting that pain felt “a little better.” Functional changes give the physician a clearer picture of whether the targeted pathway is relevant to daily limitations.
Avoid judging the result solely by how you feel while resting. A diagnostic block is intended to test the pain pattern you normally experience. Following the post-procedure instructions while safely recreating usual aggravating activities can provide the most clinically useful information.
How Physicians Interpret the Response
There is no single response that applies to every type of block or every treatment plan. In general, substantial relief that matches the expected duration of the anesthetic supports the targeted structure as a likely contributor to pain. The degree of improvement required before moving to the next treatment can depend on the condition, insurance requirements, and the procedure under consideration.
In some cases, a physician may recommend a second confirmatory block. This is especially common before radiofrequency ablation for facet-mediated pain. Repeating the test can reduce the chance of proceeding with a longer-lasting intervention based on a misleading first result.
An incomplete response does not mean the pain is not real or that no treatment options remain. It may mean the pain is coming from several sources, the block did not reach the intended target as expected, or the original diagnosis needs refinement. Persistent pain often requires this kind of careful clinical reasoning rather than a one-size-fits-all solution.
Benefits and Limitations of Diagnostic Nerve Blocks
The central benefit is precision. A well-chosen diagnostic block can help direct treatment toward a specific nerve or joint, potentially reducing unnecessary procedures, prolonged medication use, or referrals that do not address the actual source of symptoms. It can also support a more individualized decision about whether options such as radiofrequency ablation, joint-focused treatment, rehabilitation, or another intervention are appropriate.
The limitation is that no diagnostic test is perfect. Pain can fluctuate naturally from day to day. Anxiety, temporary rest after the procedure, medication effects, and the spread of anesthetic can influence the result. That is why experienced pain specialists interpret the block in the context of the patient’s symptoms, physical examination, imaging, and functional goals rather than relying on one data point alone.
Like any injection, diagnostic blocks carry potential risks, although serious complications are uncommon when performed with appropriate technique and imaging guidance. Possible effects include soreness, bleeding, infection, allergic reaction, temporary numbness, or an increase in pain for a short period. A physician should review personal risks and answer questions before treatment.
A More Focused Path Forward
For patients whose pain has persisted despite conservative care, the goal is not simply to perform another procedure. It is to obtain actionable answers. At Global Pain Solutions, diagnostic testing is considered alongside the full clinical picture so treatment decisions can support safer movement, greater independence, and better day-to-day function.
If your pain has made work, sleep, exercise, or ordinary activities more difficult, a focused evaluation can help clarify whether a diagnostic nerve block is an appropriate next step. The most useful treatment plan begins with identifying what your body is trying to tell you and choosing care that responds with precision.