
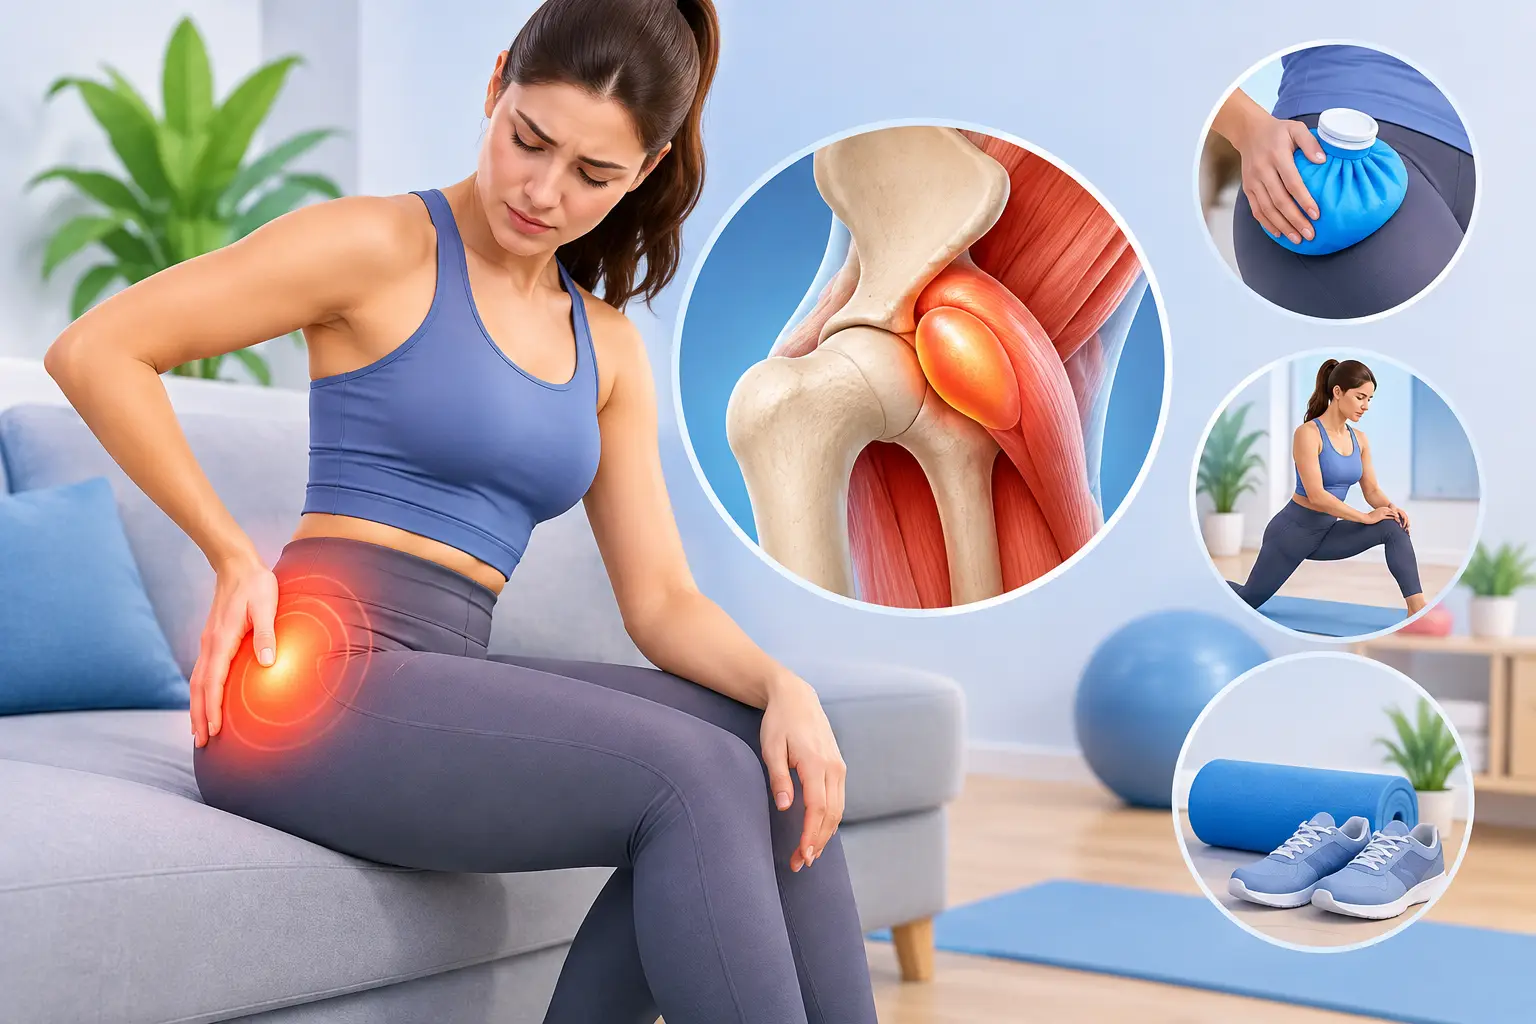
Pain on the outside of the hip can turn ordinary movements into calculated decisions. You may brace before getting out of a car, avoid a favorite walking route, or wake up whenever you roll onto one side. Although it is commonly called hip bursitis, the source of pain is not always a simple inflamed bursa. A precise diagnosis matters because the most effective treatment depends on what is irritating the tissues around your hip.
What Hip Bursitis Actually Means
Bursae are small, fluid-filled sacs that reduce friction where tendons, muscles, and bone move against one another. Around the outside of the hip, the greater trochanter is a bony prominence that serves as an attachment point for several muscles and tendons. The bursa in this area can become irritated and painful.
Many people use the term hip bursitis to describe any pain over the outer hip. Clinically, this problem is often part of a broader condition called greater trochanteric pain syndrome. In addition to bursal irritation, it may involve strain or degeneration in the gluteal tendons, weakness in the hip stabilizing muscles, altered walking mechanics, or pressure from lying on the affected side.
That distinction is more than medical terminology. A treatment plan aimed only at inflammation may provide limited or temporary benefit when tendon overload, spine-related pain, arthritis, or another condition is contributing to the symptoms.
Common Signs of Hip Bursitis
The classic symptom is tenderness on the outside of one hip. The area may hurt when pressed, and pain can travel down the outside of the thigh. Unlike pain from the hip joint itself, which is often felt in the groin or front of the thigh, trochanteric pain is usually more lateral.
Symptoms often become more noticeable with activities that load the hip or require the pelvis to stay stable on one leg. Walking uphill, climbing stairs, standing for long periods, crossing the legs, and getting up from a low chair can all aggravate the area. Lying on the painful side is particularly common, and some people also feel discomfort when lying on the opposite side if the top leg drops forward and stretches the outer hip.
Pain may begin after a change in activity, such as starting a new exercise program, increasing walking mileage, or returning to activity after an injury. It can also develop gradually without one clear event. Women, adults over age 40, runners, people with leg-length differences, and those with low back, knee, or hip conditions may be more susceptible, but the condition can affect anyone.
When Outside Hip Pain May Be Something Else
Not all hip pain belongs to the bursa. Hip osteoarthritis may cause groin pain, stiffness, and difficulty putting on shoes or getting in and out of a vehicle. Lumbar spine conditions can produce pain, numbness, tingling, or weakness that travels into the leg. Sacroiliac joint dysfunction, muscle injuries, and some nerve conditions may also feel like pain around the hip.
This is why a thorough evaluation is valuable, particularly when symptoms persist despite rest or keep returning. Treating the location of pain without identifying the pain generator can lead to frustrating cycles of short-lived relief.
Why Hip Bursitis Can Linger
A bursa can become irritated after direct pressure or overuse, but ongoing symptoms frequently reflect a load-management problem. The hip muscles must control the pelvis every time you take a step. If the gluteal tendons are overloaded, weak, or not coordinating well with the surrounding muscles, the outer hip remains under stress even during routine activities.
Sudden increases in walking, running, hill training, or standing can exceed what the tissues can tolerate. On the other hand, long periods of inactivity can reduce conditioning and make a return to movement more difficult. Body mechanics, footwear, prior joint injury, and pain-related changes in how you walk can also contribute.
There is a practical trade-off here: complete rest may calm symptoms briefly, but prolonged avoidance can reduce strength and confidence in movement. Pushing through sharp or worsening pain is not the answer either. The goal is usually to reduce aggravating load while gradually rebuilding the hip’s capacity.
How a Pain Specialist Evaluates Outer Hip Pain
An effective evaluation begins with your story. When did the pain start? Is it worse on stairs, after sitting, or at night? Does it stay at the outer hip, or does it radiate below the knee? Have you noticed weakness, numbness, fever, swelling, or a recent fall?
A focused physical examination can help distinguish tenderness over the greater trochanter from pain coming from the hip joint, low back, sacroiliac joint, or surrounding muscles. Your clinician may assess your gait, hip range of motion, muscle strength, balance, and the movements that reproduce symptoms.
X-rays may be useful when arthritis, fracture, or structural changes need consideration. Ultrasound or MRI may be appropriate when symptoms are persistent, the diagnosis is uncertain, or a tendon tear or other soft-tissue condition is suspected. Imaging supports the clinical picture, but it should not replace a careful examination. Many imaging findings are common in people without pain, so results need to be interpreted in context.
Treatment for Hip Bursitis: A Personalized Path
Most people do not need surgery for outer hip pain. Care generally starts with conservative measures, then becomes more targeted if pain continues to limit sleep, work, mobility, or rehabilitation.
Activity modification does not mean stopping all movement. It may mean temporarily reducing hills, high-impact exercise, deep squats, or other triggers while maintaining comfortable activity. Avoiding prolonged pressure directly over the painful side can help. Some people sleep more comfortably on the opposite side with a thick pillow between the knees, or on their back with support under the knees.
Physical therapy is often central to durable improvement. A well-designed program can address hip abductor strength, pelvic control, balance, flexibility where appropriate, and movement patterns that repeatedly overload the outer hip. Exercises must be selected carefully. Some aggressive stretching positions can compress irritated tissues and worsen lateral hip pain, especially early in recovery.
Anti-inflammatory medication may be appropriate for some patients, depending on their medical history and other medications. It is not suitable for everyone, including people with certain kidney, gastrointestinal, heart, or bleeding risks. Medication can reduce symptoms, but it should support an overall plan rather than become the only plan.
When an Injection May Be Considered
If conservative care has not provided enough relief, a targeted injection may be an option. Image-guided treatment can help a pain specialist place medication accurately around the inflamed bursa or other suspected pain-generating structures. Reducing pain may make it easier to sleep, walk, and participate effectively in rehabilitation.
An injection is not a cure for every cause of lateral hip pain. If gluteal tendon dysfunction, joint arthritis, or pain referred from the spine is the primary issue, the treatment strategy may need to change. The expected duration of relief also varies from person to person. A thoughtful plan weighs potential benefits against risks and uses response to treatment as useful diagnostic information.
At Global Pain Solutions, care is guided by the principle that pain relief should serve a larger goal: restoring safe, meaningful function. For some patients, that means returning to work without limping. For others, it means sleeping through the night, walking the dog, traveling comfortably, or remaining active with family.
When to Seek Prompt Medical Care
Outer hip pain should be evaluated urgently after a significant fall or injury, especially if you cannot bear weight. Prompt care is also warranted for fever, chills, redness or warmth around the hip, rapidly increasing swelling, unexplained weight loss, severe unrelenting pain, or new numbness or weakness in the leg. These symptoms may point to a problem other than routine bursitis.
If pain has lasted several weeks, disrupts sleep, or keeps returning despite reasonable self-care, it is worth seeking a more complete assessment. Persistent hip pain is not a sign that you simply need to tolerate less activity. With an accurate diagnosis and a plan built around your needs, the next step can be moving with greater comfort and confidence again.